Pharming Group reports third quarter 2025 financial results Just as expected. The story continues!
3 Likes
It looks quite good. If strong growth continues again next year, at some point the share price will have to reflect that. Q4 seems to be a bit slower in terms of growth according to the new positive guidance, so let’s hope for new positive guidance in December:
- 2025 total revenue guidance raised to US$365 - US$375 million, up from prior US$335 - US$350 million.
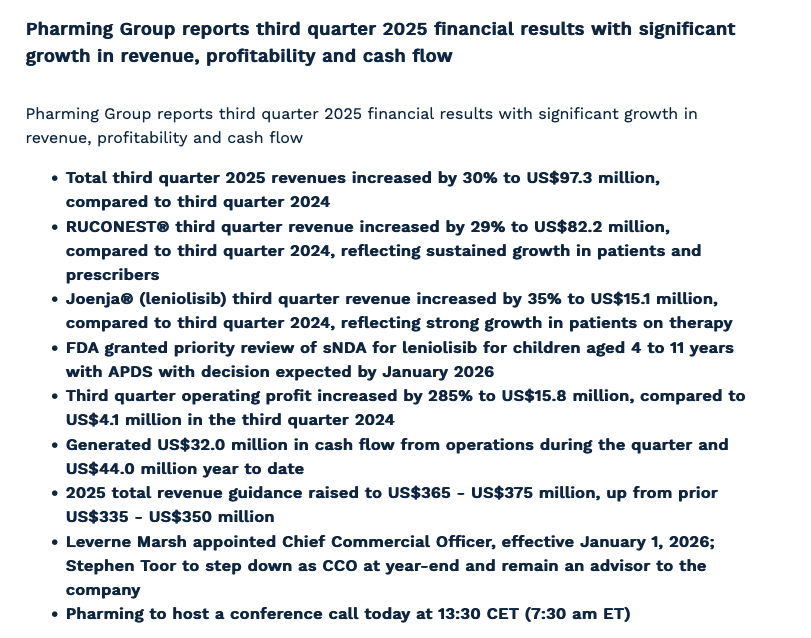
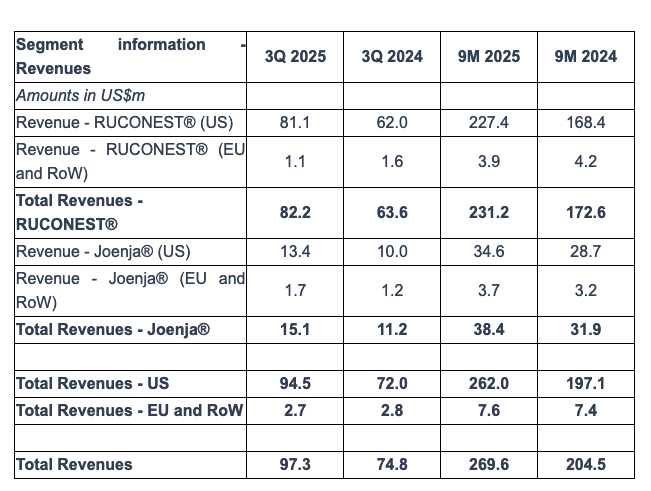
It will slow down a bit in the coming quarters, as they decided to withdraw Ruconest from outside the US:
Pharming has made the strategic decision to withdraw RUCONEST® from registration and/or commercialization in all non-US markets. These markets contributed only US$1.1 million, or 1.3% of total RUCONEST® revenue in the current quarter and have never demonstrated financial sustainability. Ensuring continuity of care and minimizing the impact on patients during this transition remain our highest priorities. This decision also enables Pharming to reallocate resources toward pipeline opportunities with greater long-term growth potential.
For Joenja, growth is almost guaranteed for next year as well:
APDS patient finding
As of September 30, 2025, we have identified 990 diagnosed APDS patients of all ages globally, including 270 patients in the U.S. Of the identified patients in the U.S., 175 patients are 12 years of age or older and currently eligible for treatment with Joenja®, while 54 are between 4 and 11 years of age and would become eligible pending regulatory approval expected in January 2026.
VUS patient reclassification
There are currently over 1,400 known U.S. patients with a variant of uncertain significance, or VUS, in the PIK3CD and PIK3R1 genes implicated in APDS. We estimate that 20% of VUS patients could ultimately be diagnosed with APDS, thereby expanding the addressable patient population for Joenja®. Genetic testing laboratories are currently evaluating data from a study published in June 2025 in the leading peer-reviewed journal Cell, by researchers at Columbia University, to determine the process and potential to reclassify patients to APDS.
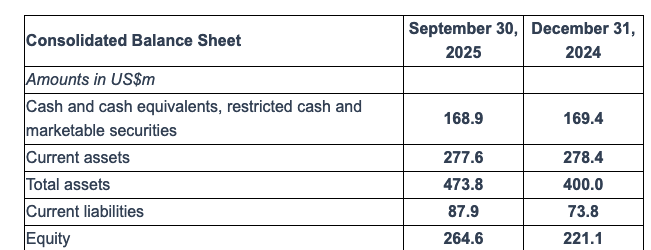
There’s money:
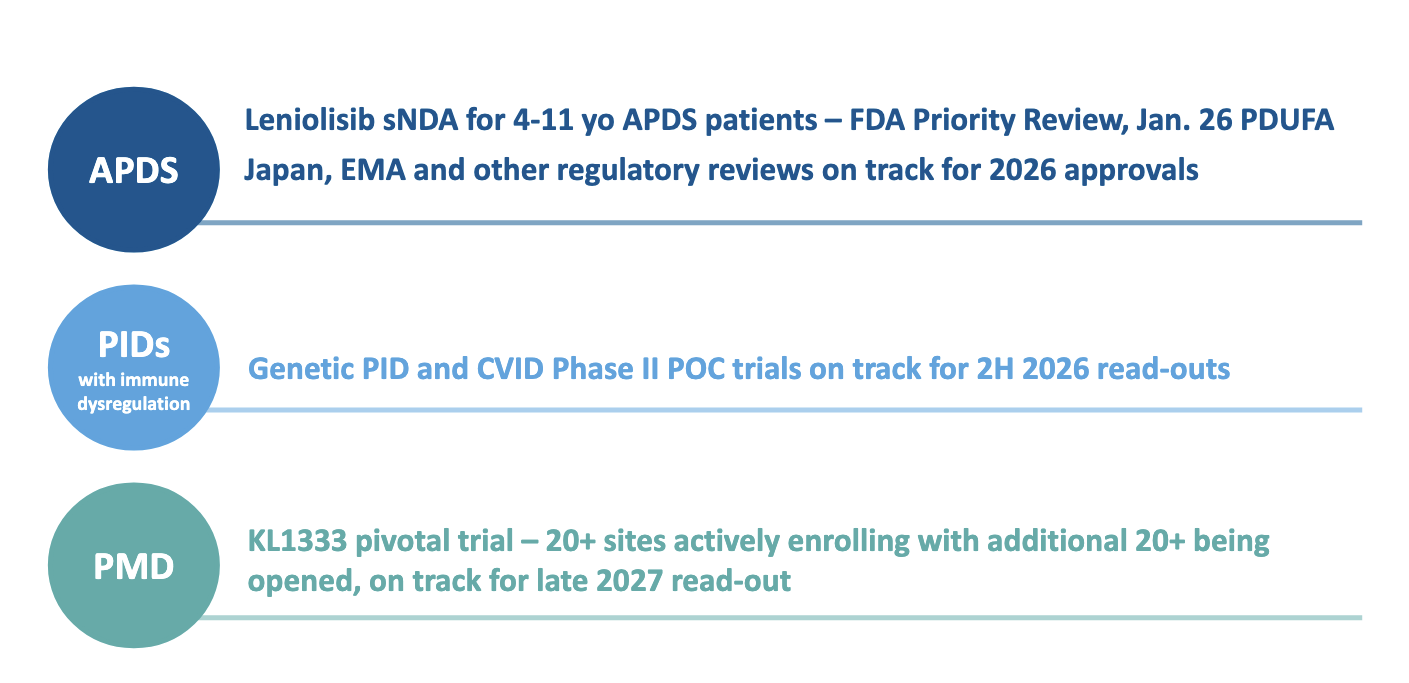
Plenty of catalysts:
Slides:
16 Likes
There’s probably some political risk here, because even though the high cost of medicines is the only reason treatments are developed for such conditions and the option of an “affordable medicine” doesn’t exist with current technology, that doesn’t stop politicians from promising such things and dictating some maximum price or maximum margin, etc. Let’s not get into politics now, but it’s probably one risk, but no more on that.
The question is, how do the sales of these expensive medicines work? So, if, for example, KL1333 finds a market of tens of thousands of patients, is the assumption that a significant portion of them would start using it within a couple of years of the drug’s launch (assuming results, approval processes, etc., go well)? Or does it work more like this: a drug costing a 6-figure sum per year is given to a relatively small group in the first year, a slightly larger group in the next, and a slightly larger group the year after that, etc., so that growth could be good double-digit percentage growth, but not such that sales would rise from zero to hundreds of millions in a couple of years? At least with Joenja, it seems that sales started in 2023 and the growth rate is certainly strong, but will it then stabilize around just over 20%?
For the company’s business itself, the gross margin is indeed very high, and sales have grown at a good pace, but costs also seem to be increasing. So, is the forecast that sales growth will only accelerate, or that cost growth will stop/slow down? It’s certainly an interesting company, but I’d need to find time somewhere to properly delve into it.
2 Likes
There is definitely a political risk, a customs risk, and a country risk for the United States. In addition, there is also a distributor risk, as almost all of the company’s revenue comes through two distributors. Politically interfering with compensation levels would kill the entire global drug development market, but dire consequences have never before been an obstacle to a political decision. Some speculate that the discontinuation of Ruconest sales outside the United States would be a countermove to Trump demanding pharmaceutical companies supply drugs to the country as cheaply as to other countries. Well, if it’s not supplied elsewhere, then the price is the cheapest possible 
Regarding Joenja, it’s good to know that APDS was only discovered in 2013, and initially, it was expected to affect only about 500 patients in the United States. This equation meant that no hyperscaling was possible, as those patients really had to be searched for with a fine-tooth comb in a large country, and the medical machinery had to make the correct diagnosis in a country where citizens fear seeking treatment due to its cost. The fastest growth rate for Joenja is only just beginning now, so for next year, I would consider +40% growth more likely than +20% growth. However, the disease is still so new that we don’t yet know how common it is in the world’s population and which variants Joenja works on, so additional growth will come as research is completed. The drug has enormous potential, of which only a fraction has been seen.
For KL1333, scaling is significantly easier and faster than Joenja, because mtDNA-mediated primary mitochondrial disease has been known for longer, and patient numbers are considerably larger and more medically concentrated. This is a direct blockbuster drug if its efficacy and safety can be demonstrated. If not, the value is likely to be around zero.
Regarding costs, I would actually predict that costs will accelerate even faster than sales for the next 1.5 years. This is a fairly common problem for young pharmaceutical companies, where building a sales and marketing machine costs the same whether one drug or ten drugs are being sold, and the costs of drug development and regulatory applications must be paid almost in full in advance before any money comes into the account. Therefore, Ruconest doesn’t really generate anything for the investor’s pocket but solely acts as a cash flow generator for the ramp-up of Joenja and KL1333, as well as for new acquisitions. This also increases the riskiness of the investment, as the success of these new drugs is not optional in terms of the investment story, and the majority of the company’s value is still captive to successful drug trials.
The cost structure is generally at a healthy level, as the majority of funds go to sales & marketing and research & development, i.e., future growth investments:
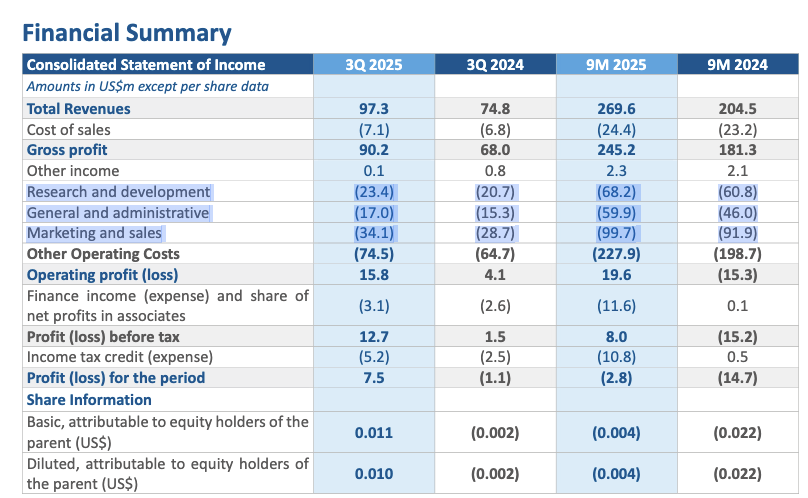
In addition, savings are being made in administrative costs, which will materialize next year. This company is certainly not celebrating with investors’ money:
Pharming Group provides update on previously announced G&A expense reduction plan October 6, 2025
The restructuring is aligned with our previously announced plan to reduce general and administrative (G&A) expenses to optimize capital allocation across the organization.
The restructuring includes a redesign of Pharming’s organizational structure and a 20% net reduction in non-commercial and non-medical headcount, primarily at our Netherlands headquarters. We remain on track to reduce total G&A expenses by 15% or US$10 million annually and anticipate one-time restructuring costs of approximately $7 million to be recorded in the fourth quarter of 2025 in connection with the headcount reduction.
What new growth will this money bring on top of conventional sales work? The pipeline certainly includes for the next two years at least:
Joenja marketing authorization for children aged 4-11.
Joenja marketing authorization for the European Economic Area.
Joenja marketing authorization for Japan.
Joenja expanded use study for VUS patients.
Joenja expanded use study for PID patients.
Joenja expanded use study for CVID patients.
KL1333 pivotal study in PMD patients.
The company’s management has also indicated a desire to continue investments beyond these and build a larger-scale pharmaceutical company specializing in rare diseases. Of course, growth costs money, but it would be even more expensive for investors if growth were not invested in and some dividends were distributed too early 
10 Likes
New competitors are coming for Ruconest off the assembly line:
DAWNZERA™ (donidalorsen) was approved on August 21, 2025, by the FDA for prophylaxis to prevent attacks of hereditary angioedema (HAE) in adult and pediatric patients 12 years of age and older
U.S. launch underway and off to an encouraging start
Pharming’s current workhorse cannot grow by large percentages forever, and even though there is still future growth in the pipeline, by next year, the sales responsibility will presumably already shift to the exclusive drug Joenja, for which there is no competition.
7 Likes
1.5€ and a billion valuation broken 
The following catalysts are:
-
Joenja, in the coming months, Phase III results on efficacy and safety for 1-6 year olds.
-
Joenja, approval in the United States for 4-11 year olds, FDA PDUFA Priority Review Jan 31, 2026, after which a positive decision could allow sales to begin as early as Q1 2026.
-
Joenja, fulfillment of production requirements set by European authorities and successful submission of the marketing authorization application by January 2026 at the latest.
-
Joenja, approval for 4+ year olds in Japan during Q1 2026 or Q2 2026.
-
Joenja, as a wildcard, approval for 12+ year olds in Canada, South Korea, and Saudi Arabia, whose approval processes do not yield similarly predictable dates and which may also occur during H1 2026.
With this news flow, I wouldn’t be surprised if we soon touched stronger two-euro levels
14 Likes
C1 inhibitor such as Ruconest is the primary drug for short-term HAE prophylactic treatment according to treatment guidelines. Additionally, C1inh is mentioned first on the list of acute treatment drugs. Ruconest’s comfortably continuous growth implies that it is taking market share from the established but old-fashioned (plasma-derived) C1 inhibitor Berinert.
I know that Berinert and Firazyr are used in Finland, but this is so-called useless information, because we are only interested in what happens in the USA.
4 Likes
Pharvaris announced strong data; this will likely outperform Ektery.
My view is that these effective oral on-demand treatments reduce the number of people ending up in the hospital. But some always end up in the hospital, and there, intravenous medication is preferred. I’m getting the impression that Berinert and Ruconest are the best options here. An airway-obstructing HAE attack is no joke; in such a situation, the best and fastest-acting medication is wanted. I understand why Ruconest may have gained a foothold in the market – in the USA, there’s some paranoia regarding plasma-derived products (theoretical risk of HIV and hepatitis transmission). Another area where Ruconest is strong is short-term prophylaxis (given, for example, before surgery).
3 Likes
JOENJA’s PDUFA date for the label expansion to 4-11 year olds is January 31. The decision may come earlier.
The study on which the expansion application is based has been published here.
The drug was tested without a control group in 21 patients. The safety profile was very clean, with no grade 3 or more serious adverse effects. The dosage was weight-based, 20-70mg twice daily. The adult dose is 70mg twice daily.
The endpoints examined were the change in lymph node size (SPD) and the normalization of naive B-cell counts over a 12-week period.
SPD was -0.19 on a log10 scale, i.e., 10^-0.19 = 0.64 = a 36% reduction.
The change in the number of B-cells was 33.3%.
The endpoints are therefore the same as in the original adult phase 3 study, and the efficacy readings are of a similar magnitude.
With this data, I believe the FDA will grant approval for this orphan drug in the 4-11 age group as well.
8 Likes
A very minuscule positive profit warning from Pharming Group, but every little bit helps:

6 Likes
They should have at least hyped this in the headline; I just ended up reading the headline because I thought this was just a basic schedule for the interim report. It’s significant in that sense, though, as there has been so much fear going around about Ruconest’s total collapse toward the end of the year because of Ekterly.
2 Likes
I personally think that Ruconest is primarily taking market share from the old-fashioned Berinert. Ekterlyn, which is a tablet, has its niche in self-care for cases with milder symptoms.
Intravenously administered treatments will always be needed. If a patient is brought to the hospital with blocked airways, tablets probably won’t help there…
And there must ALWAYS be a SUFFICIENT supply of these medicines in stock.
4 Likes
What do you think about DAWNZERA™, if the attacks themselves are significantly reduced?
2 Likes
Yes, hospitalizations decrease as more widespread and effective preventive treatments are used. But for acute care, Ruconest/Berinert is number one.
3 Likes
No approval for Joenja for 4-11 year olds 
The FDA raised an issue with the potential for underexposure in lower weight pediatric patients. As a result, the FDA has requested additional pediatric pharmacokinetic data to reassess the proposed pediatric doses and confirm that children in the lower weight dose groups can achieve exposure levels comparable to the approved adult and adolescent regimen. The letter also identified an issue with one of the analytical methods used for production batch testing, and the FDA requested additional data and clarification on this point.
We believe we can address the clinical pharmacology and batch testing methodology issues outlined in the letter, and we plan to work closely with the FDA to meet the Agency’s requirements and determine next steps for resubmission. We plan to request a Type A meeting with the FDA.
Joenja’s U.S. FDA approval for the treatment of APDS in patients aged 12 years of age and older is unaffected by this regulatory action.
4 Likes
Sounds like a nothingburger. The FDA isn’t raising concerns that would require new efficacy studies. However, time is being wasted and revenue is being pushed further out, so tomorrow the stock will likely be available slightly cheaper.
5 Likes
It could be a volatile couple of days, as there is still an investor day tomorrow where guidance for this year might be provided: Pharming Group reports preliminary 2025 revenues and announces Investor Day | Pharming Group N.V.
3 Likes
Investor Day highlights:
The FDA decision was a disappointment, but they are aiming to arrange the next FDA meeting in March to remove hurdles for the approval of Joenja for 4–11-year-olds. They don’t know yet whether this can be resolved with current data or if more studies will be required.
2026 guidance:
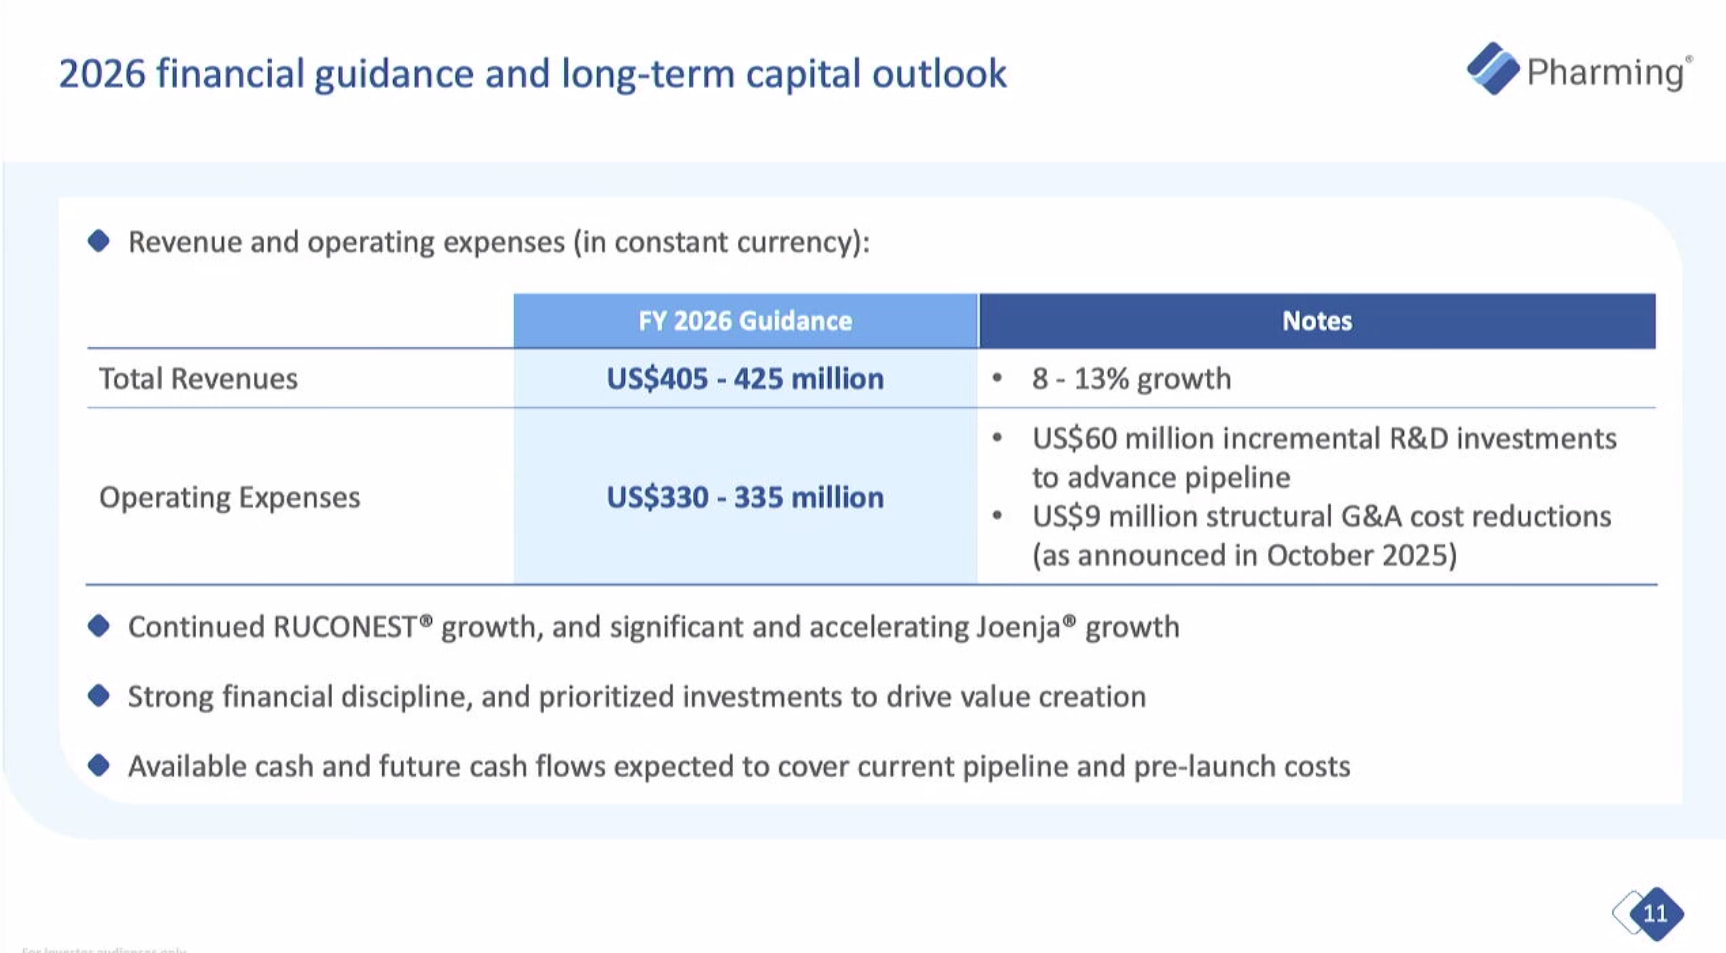
Quite conservative, as the sales of Joenja for young children are delayed, but it certainly allows for positive profit warnings to be issued later in the year. Ruconest really can’t afford to underperform if the guidance is to be met.
12 Likes
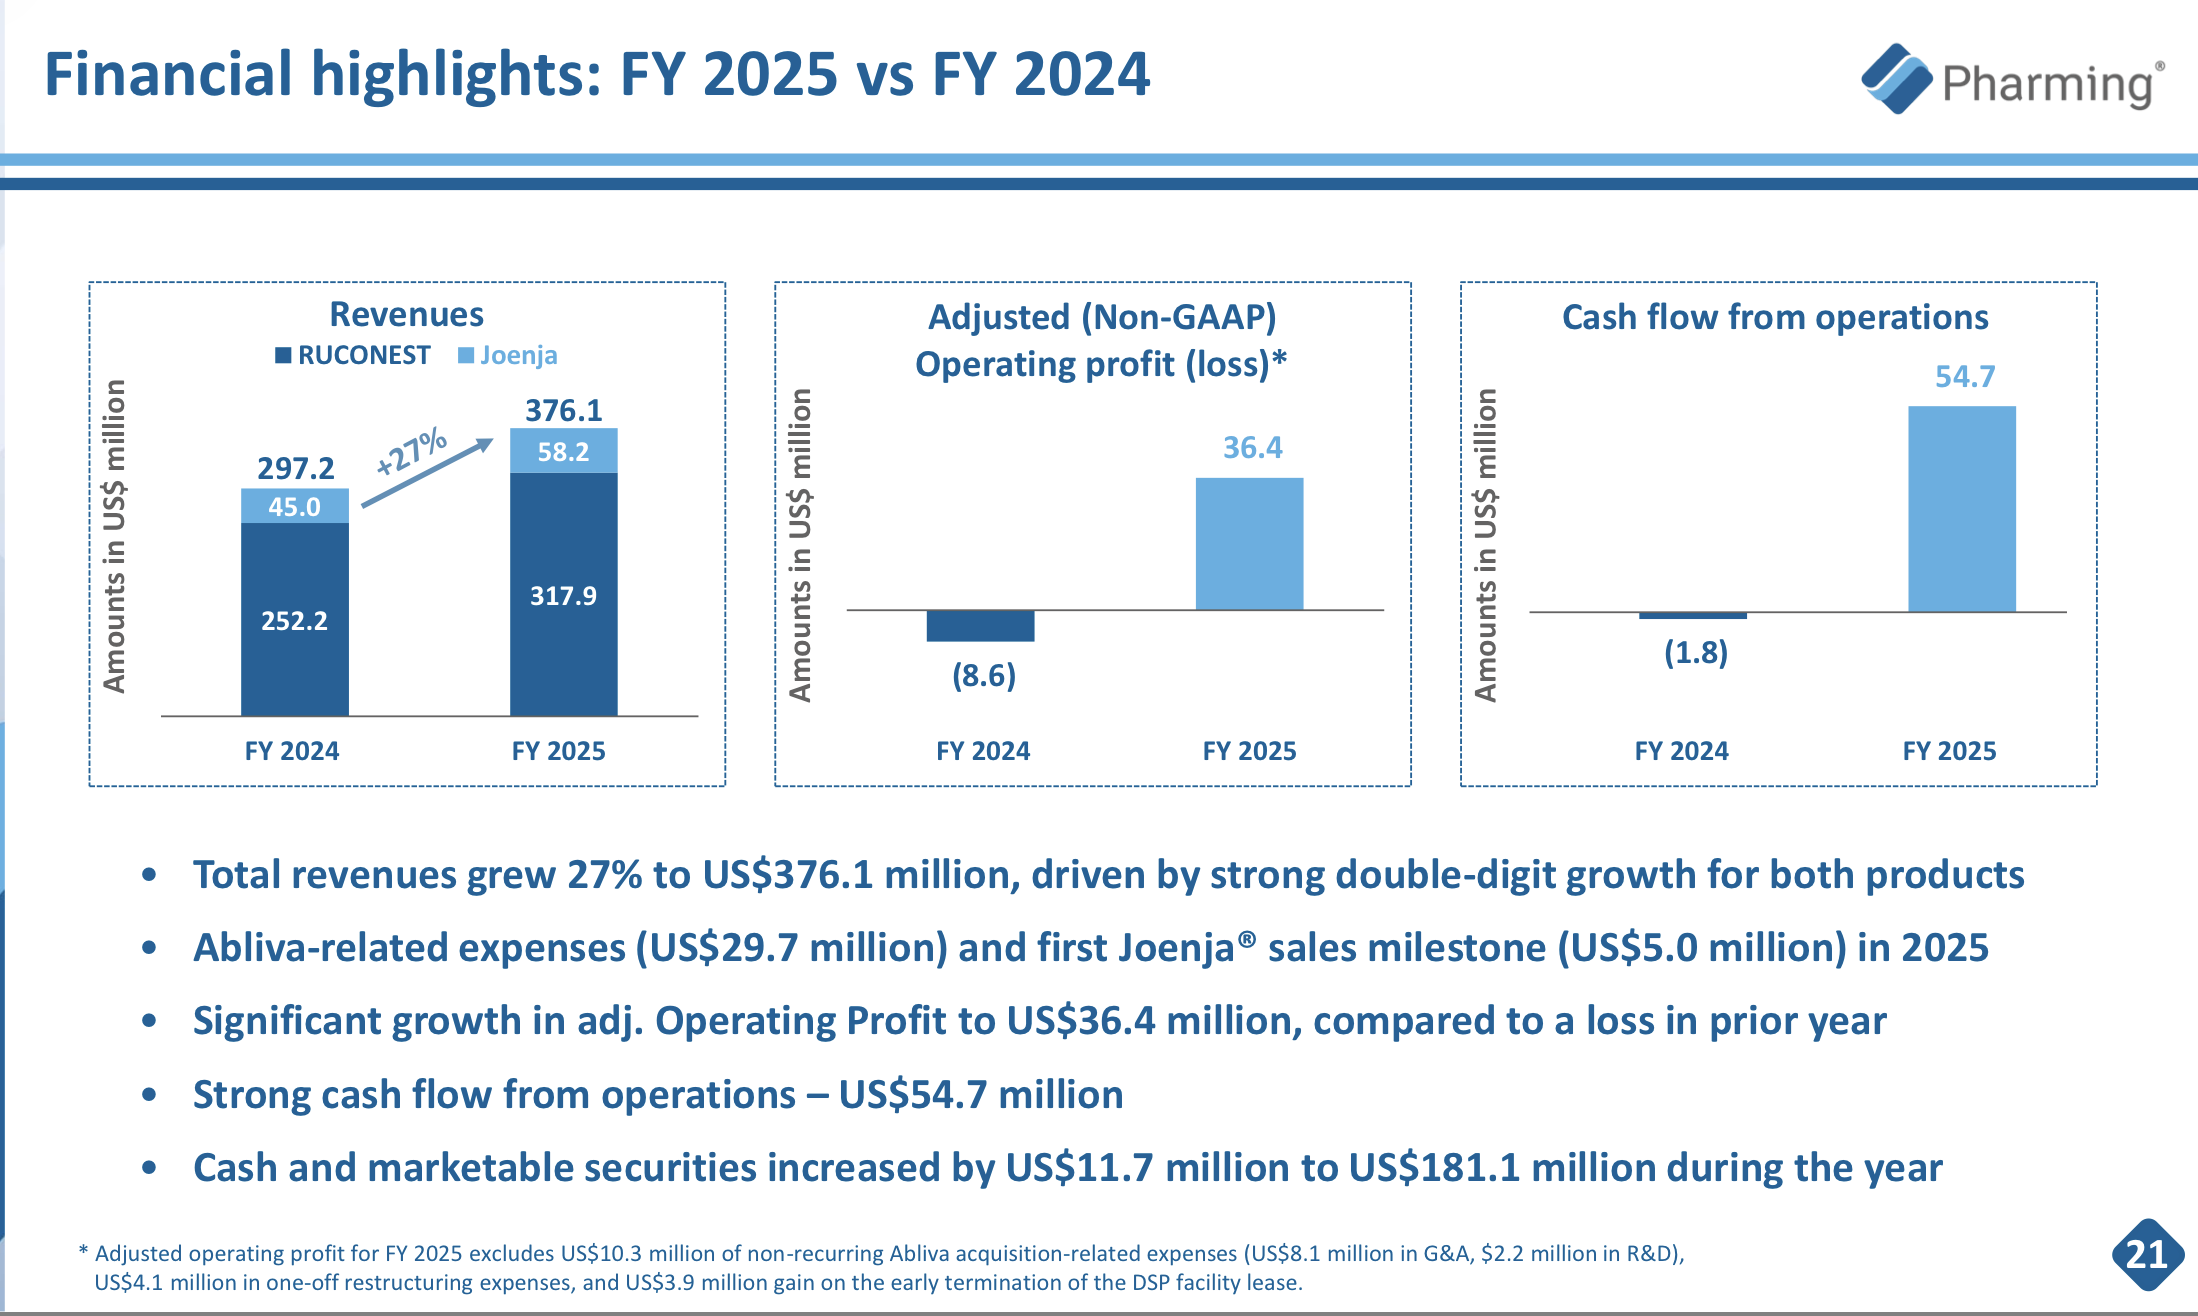
Q4 is out. There was a small positive profit warning, but otherwise no major surprises. The company is now strongly profitable and generates strong positive cash flow on top of a large cash balance:
The product pipeline is progressing, and while waiting for new medical solutions, revenue growth is expected to slow down to around ten percent:
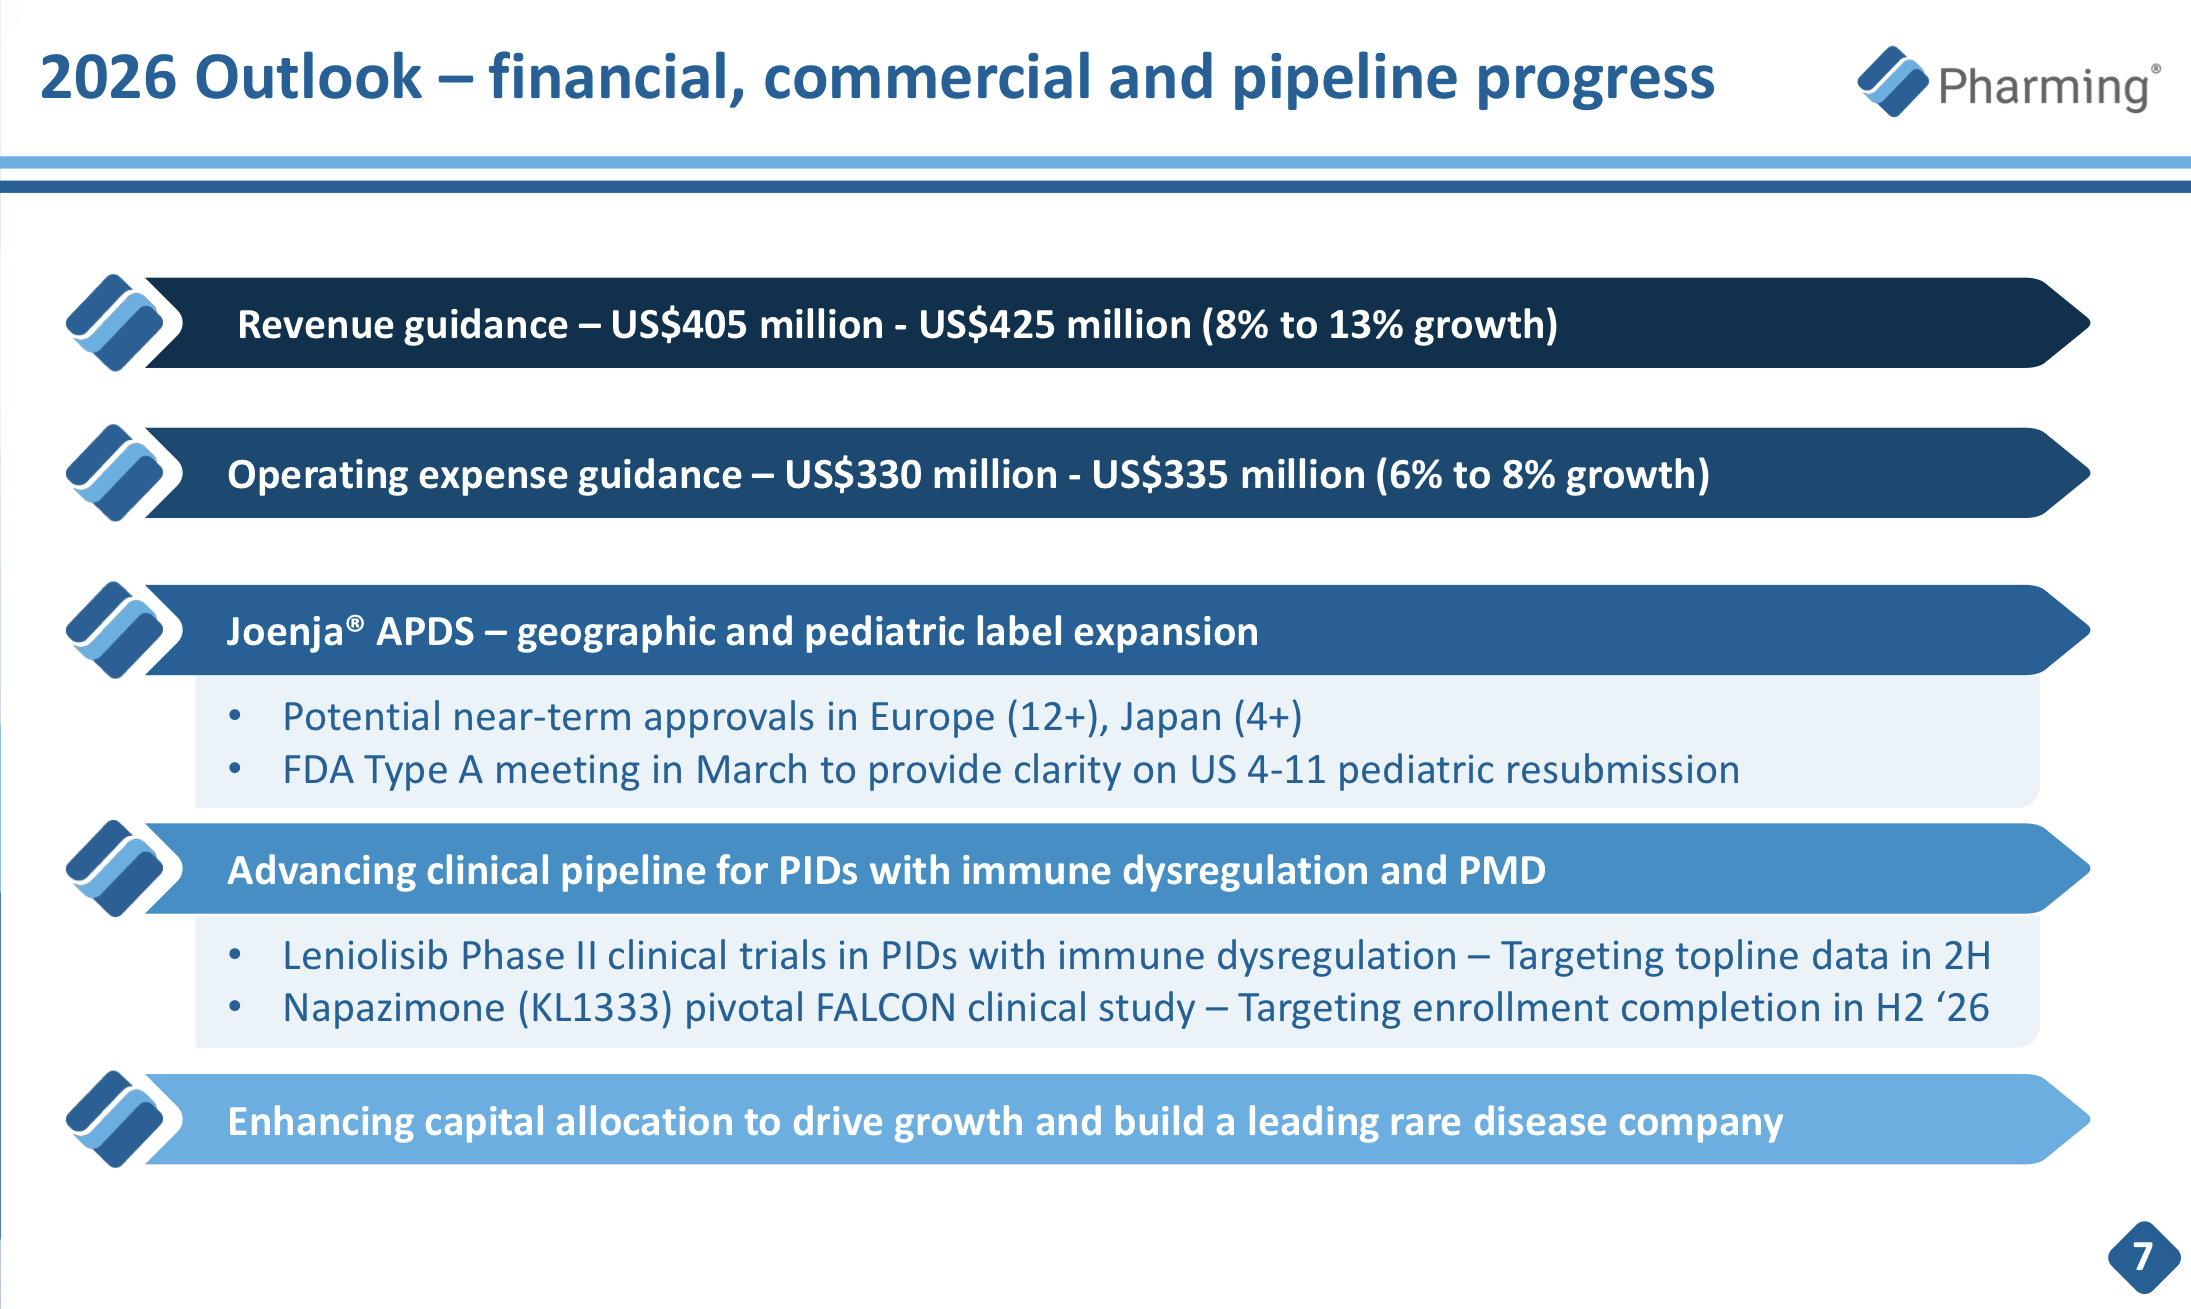
Regarding Joenja’s age limits and geographical expansions, follow-up discussions with the U.S. FDA are expected within this month, and a (positive) announcement is also expected from Japan’s PMDA. Around mid-year, there should be announcements regarding decisions from Europe’s EMA and Canada’s CMC:
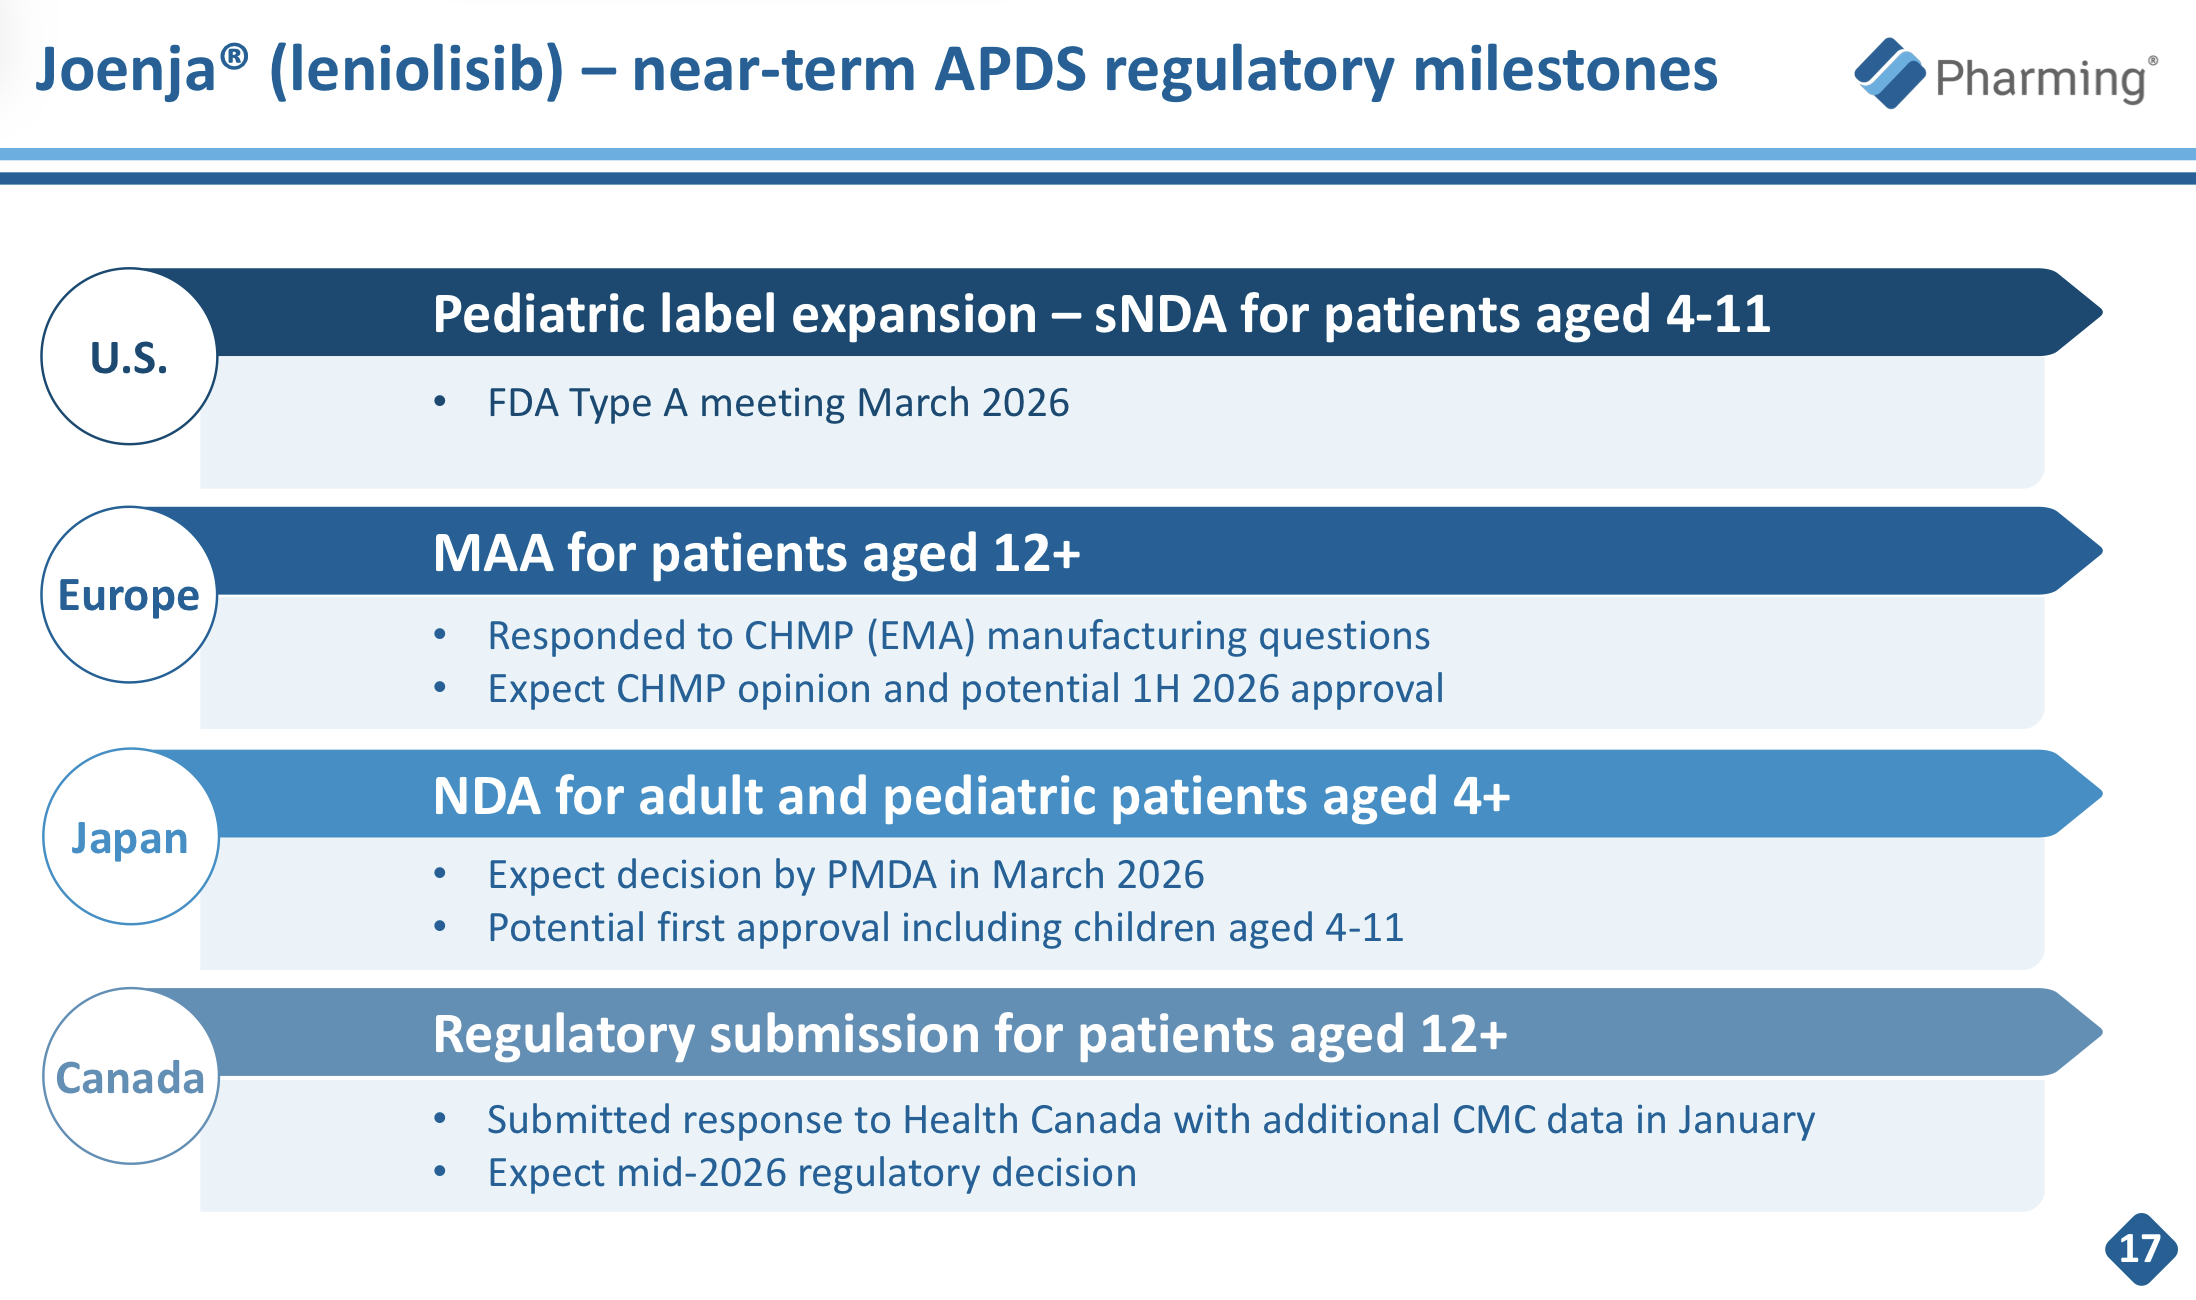
Waiting for further announcements and news to be published soon:

8 Likes
Thank you, Japan!
Pharming Group announces approval of Joenja® (leniolisib) in Japan for the treatment of APDS in patients aged 4 years and older
Pharming Group N.V. today announced that Japan’s Ministry of Health, Labour and Welfare (MHLW) has approved Joenja® (leniolisib), an oral, selective phosphoinositide 3-kinase (PI3K) delta inhibitor, for the treatment of activated PI3K delta syndrome (APDS) in adult and pediatric patients aged 4 years and older.
- First approved treatment in Japan for activated phosphoinositide 3-kinase delta (PI3Kδ) syndrome (APDS)
- Approval is based on positive Phase III data from multinational and Japanese studies in patients aged 12 years and older and a multinational pediatric study in children aged 4 to 11 years
- First approval of Joenja covering children aged 4 to 11 with APDS
At least AI estimates approximately 40-80 patients in Japan in that age group. I don’t know if the company has estimated this itself in any presentations?
4 Likes